
What are Large Volume Parenterals?
Large Volume Parenterals (LVPs) are sterile parenteral preparations supplied in relatively large-volume containers, typically intended for intravenous infusion. The exact volume threshold may vary according to the applicable pharmacopoeial or regulatory framework.
Unlike Small Volume Parenterals (SVPs), which are generally administered as a bolus or over a short period, LVPs are designed for continuous or prolonged infusion, in quantities that directly affect the patient’s fluid, electrolyte and nutritional balance.
Therefore, because these products bypass the body’s physiological barriers and enter the bloodstream directly, quality requirements are particularly stringent:
- sterility and absence of bacterial endotoxins (LAL test),
- control of visible and sub-visible particles,
- osmolarity and pH compatible with administration,
- compatibility between the solution and its packaging material (glass, polyolefins, PVC, multilayer systems).
Hence, where the stability of the formulation allows, these products are generally autoclaved in their final container (terminal sterilisation).
Main types of LVP Solutions
For clinical and technological purposes, LVPs fall into three main categories:
1. Fluid and Electrolyte Balance
This category includes solutions intended to restore or maintain fluid and electrolyte homeostasis, which is essential for cellular function, osmotic pressure, acid-base balance and tissue perfusion. The main families are:
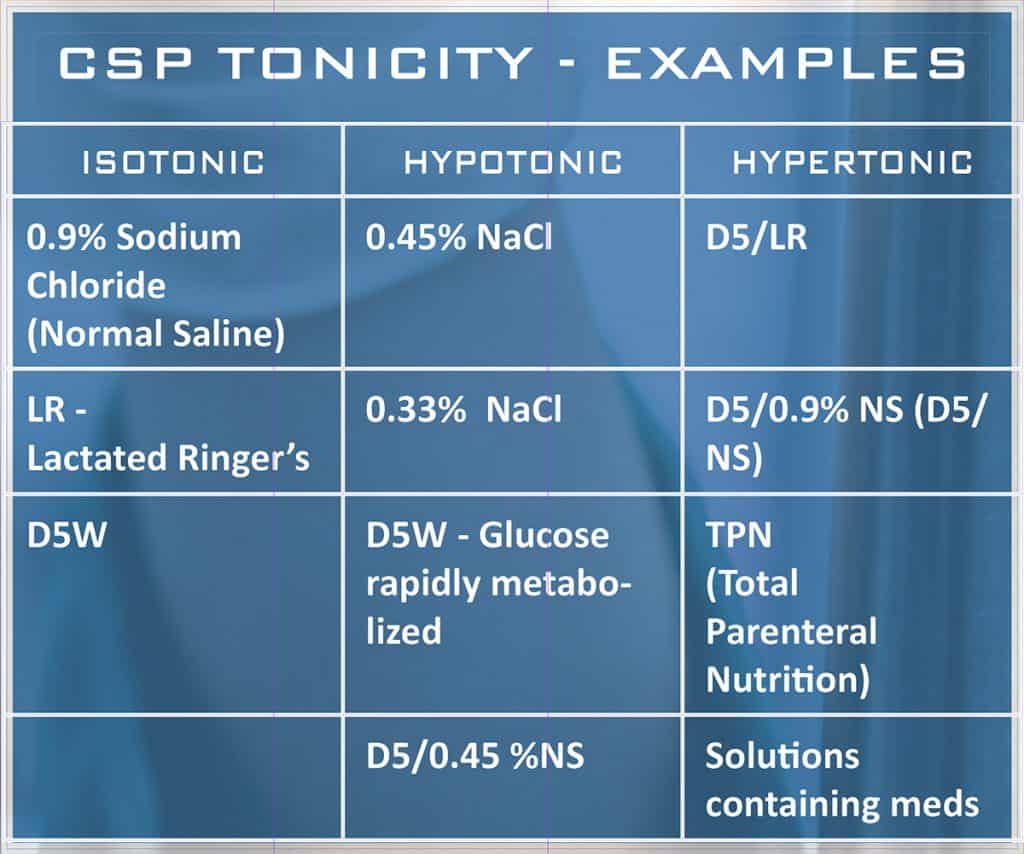
- Isotonic and balanced crystalloids: physiological saline (0.9% NaCl), lactated Ringer’s (Hartmann’s) solution, Ringer’s acetate and balanced multi-electrolyte solutions, whose ionic composition is closer to that of plasma. They are used for rehydration, maintenance and volume expansion.
- Hypotonic and glucose solutions: 5% glucose (dextrose) and mixed glucose-electrolyte solutions, used to provide free water and a limited energy supply.
- Hypertonic and corrective solutions: hypertonic NaCl, potassium chloride, sodium bicarbonate and other solutions for the correction of specific imbalances.
- Colloids: albumin-based solutions or modified starches/gelatins, used for plasma volume expansion. The use of some synthetic colloids is now subject to regulatory restrictions and careful benefit/risk assessment.
- Solutions for renal replacement therapy (CRRT, haemofiltration), which technically fall within this area owing to their role in restoring fluid and electrolyte balance.
The choice of solution depends on osmolarity, tonicity, ionic composition, the presence of metabolisable anions (lactate, acetate) and the patient’s clinical condition.
2. Nutritional Support
When oral or enteral feeding is impossible, insufficient or contraindicated, parenteral nutrition (PN) or Total Parenteral Nutrition (TPN) delivers the macronutrients and micronutrients needed to maintain or restore nutritional status intravenously. These formulations comprise:
- Carbohydrates: mainly glucose, as the primary energy source.
- Amino acids: balanced solutions of essential and non-essential amino acids, with profiles tailored to specific populations (adult, paediatric, hepatic or renal insufficiency).
- Lipids: lipid emulsions based on soybean oil, medium-chain triglycerides (MCT), olive oil, fish oil or multi-source blends, providing essential fatty acids and a high energy density.
- Electrolytes, vitamins and trace elements, added according to requirements.
From a technological standpoint, a distinction is made between single-chamber, dual-chamber and triple-chamber systems (see TPN in this website). In the latter, the components are separated by peelable seals and mixed at the point of use, ensuring stability, fewer manipulations and a lower risk of microbial contamination than pharmacy compounding. “All-in-one” (AIO) admixtures require particular attention to stability and compatibility, especially with regard to the lipid emulsion and the presence of divalent cations.
3. Drug Delivery
LVPs also serve as vehicles for drug administration. Therefore, in this setting the container and the solution form the system for diluting, reconstituting and infusing active substances that require slow, controlled or large-volume administration. Applications include:
- Ready-to-use (RTU) premixes of antibiotics, antifungals, analgesics, anticoagulants, electrolytes and other drugs, which reduce preparation steps and the risk of error.
- Diluents for concentrated or lyophilised drugs, such as 0.9% NaCl or 5% glucose, selected according to the compatibility and stability of the active substance.
- Controlled infusion systems, for therapies requiring defined timings and flow rates, also in combination with volumetric pumps or gravity-fed systems.
The value of this category lies in patient safety, the standardisation of hospital processes and shorter preparation times, with benefits for healthcare staff.

Manufacturing of LVPs
The manufacture of Large Volume Parenterals (LVPs) is one of the most demanding areas of pharmaceutical production. Consequently, every stage, from the generation of the water used as the primary raw material to the sealing of the final container, must ensure that a product intended for direct intravenous infusion is sterile, pyrogen-free, particle-controlled and consistent from batch to batch. Moreover, because LVPs are produced in high volumes, often on continuous or semi-continuous cycles, these requirements must be met at industrial scale, with a high degree of automation, reproducibility and regulatory compliance (EU GMP Annex 1, FDA cGMP, and the relevant pharmacopoeial monographs).
Thus, a modern LVP facility is not a single machine but an integrated system of interconnected functional areas. The breadth of possible configurations is considerable: the choice of technologies depends on the product portfolio (crystalloids, parenteral nutrition, premixed drugs), the type of container (flexible bags, glass or plastic bottles, multi-chamber systems), the required capacity, the sterilisation strategy and the level of flexibility expected from the plant. The main functional areas are described below.
1. Compendial water production and distribution
Water is the most widely used raw material in LVPs manufacturing, and its quality underpins that of the finished product. Additionally, Water for Injections (WFI) must comply with the requirements of the European Pharmacopoeia and the USP, including limits for conductivity, total organic carbon (TOC), microbial content and bacterial endotoxins. A typical water system includes:
- Pre-treatment of feed water (filtration, softening, carbon adsorption, reverse osmosis, electrodeionisation) to produce purified water (PW).
- WFI generation by distillation (multi-effect or vapor compression distillation) or, where permitted by the applicable pharmacopoeial requirements, by suitable membrane-based processes (see waterforinjection.com for more details).
- Storage and distribution loops, typically in high-grade stainless steel (316L) with orbital welding, hot recirculation (usually above 65 °C) or ozonation, continuous monitoring of critical parameters and design features that eliminate dead legs and prevent biofilm formation.
- Pure Steam Generation, used for the sterilisation of tanks, piping and process equipment.

The image above shows a Bram-Cor control point for managing the transfer of compendial water to the formulation and preparation lines. On the right in the image below, a Bram-Cor Pure Steam Generator. In this water treatment room, you can also see a WFI loop on the left and a Multiple Effect Distiller on the right in the background.

2. Formulation and preparation
This is the stage in which the drug product takes shape. Raw materials (electrolytes, glucose, amino acids, lipids, active substances and excipients) are weighed, dispensed and dissolved in WFI within closed, controlled systems. Key aspects include:
- Preparation vessels and mixing systems, sized for the required batch volumes and designed for accurate dosing, uniform dissolution and, for emulsions, high-shear homogenisation. In the image below, you can see some Bram-Cor vessels – mixing/dissolution systems – with a platform housing a laminar flow hood.

- Automated dosing and weighing, with recipe management and full batch traceability, which limit operator intervention and the risk of error.
- In-process controls, such as pH, conductivity, density, osmolarity and temperature, to verify that the solution meets specification before release to filling.
- Filtration, including pre-filtration and sterilising-grade filtration where required by the process, and inert gas (nitrogen) management for oxygen-sensitive formulations.
- CIP/SIP (Clean-in-Place / Sterilise-in-Place) systems, which allow cleaning and sterilisation of the circuits without disassembly, ensuring hygiene and reducing downtime between batches.
The complexity of this area varies widely, from the preparation of simple saline solutions to the compounding of multi-component parenteral nutrition formulations and lipid emulsions, which demand tight control of stability and particle size distribution. In the image below: a detail of a classic CIP System (fixed station) by Bram-Cor SpA, with a SCADA control unit and a large vessel positioned on the left on a right-angled frame, custom-built for the production environment.

3. Bag filling and sealing
The filling area is where the solution is transferred into its final container. For flexible containers, the process is typically carried out on form-fill-seal (FFS) lines, in which a film is formed, filled and sealed within a single continuous operation, or on pre-made bag filling lines, where ready-made bags are opened, filled and closed. The main features of this stage are:
- Container and port systems, including administration and injection ports, closures and, for nutrition products, multi-chamber bags with peelable seals separating incompatible components until the point of use.
- Precise volumetric or mass-flow filling, in a controlled environment (typically Grade A within a Grade C background for terminally sterilised products, in line with Annex 1 requirements), with minimal particle generation.
- Sealing and integrity control, using automated leak testing and vision-based inspection systems.
- Multilayer, PVC-free films, selected for chemical compatibility, low extractables and leachables, gas barrier performance and resistance to sterilization.

In the image above: FAT (Factory acceptance test) of a filling line for the three-chamber bags required by TPN production (one filler, one chamber). In the background: the vessel buffer (one buffer, one filler) that ensures a constant feed for filling.
4. Sterilisation, inspection and packaging
Downstream of filling, most LVPs undergo terminal sterilisation in autoclaves, using validated cycles (steam-air mixture, water spray or water immersion) that preserve container integrity and product stability. Where a formulation cannot withstand heat, aseptic processing with sterile filtration is used instead, under more stringent contamination control. Thus, sterilised products then pass through automated inspection for visible particles, container defects and label conformity, followed by labelling, secondary packaging and palletisation, with serialisation and traceability in accordance with regulatory requirements.
LVPs and CSPs: complementary approaches to Parenteral Therapy
Compounded Sterile Preparations (CSPs) are sterile medicines prepared, typically in hospital pharmacies or centralised compounding facilities, to meet the needs of a specific patient or group of patients, such as:
- personalised parenteral nutrition,
- paediatric formulations
- patient-specific oncology preparations.
LVPs and CSPs belong to related but distinct areas of parenteral therapy and pharmaceutical preparation. Industrially manufactured LVPs (diluents, dextrose and amino acid solutions, lipid emulsions, electrolyte concentrates) are very often the starting materials of CSPs. As a result, the quality of a compounded preparation begins with the quality of the industrial product behind it. The main differences lie in:
- Scale and standardisation: validated large batches with extended shelf life for LVPs; small or single-patient batches with a high degree of personalisation for CSPs.
- Sterility assurance: most LVPs are terminally sterilised in their final container, while CSPs rely on aseptic processing and therefore carry shorter beyond-use dates.
- Regulatory framework: GMP and marketing authorisation for LVPs; pharmacy compounding standards (such as USP <797>/<800>, PIC/S and national rules) for CSPs.
Industry bridges the two worlds with:
- ready-to-use premixes and multi-chamber bags, which reduce the need for compounding,
- automated compounding systems that improve accuracy, traceability and operator safety where personalisation is still required.
In the image below: a Bram-Cor Amino acid line with preparation vessels and double filtration group; in the background: a Bram-Cor bag filling line for the three-chamber bags required by TPN production.

Both fields share the same principles: contamination control, process validation, data integrity and patient safety. On the other hand, a comprehensive approach combines industrial LVPs as a standardised, highly assured foundation with CSPs as a tailored complement, supported by solutions that connect water generation, formulation, filling, sterilization and compounding technologies.
- Technical note by Bram-Cor engineering department · updated Oct 2026 – Data may change without notice.

© Bram-Cor SpA 2018-2026